


ReviewNovember 10, 2026
Laryngeal Cleft and Speech Delay: What Every Parent Should Know
If your child was born with a laryngeal cleft, you already know how much a tiny gap in the airway can take over family life. Feeding takes forever, coughing fits seem to come from nowhere, and every cold feels like a crisis. Then, somewhere around the second birthday, a new worry arrives: why isn't my child talking like other kids? At Stop Stuttering, parents ask us this more often than you'd think, and the honest answer is that laryngeal cleft and speech delay are connected in several quiet ways.
In this guide, we'll walk through what a laryngeal cleft actually is, why it can slow down speech, and what the brain has to do with all of it. We'll keep the language simple and the advice practical, because you've probably read enough medical jargon already.
One thing up front. A laryngeal cleft is a medical condition, and it needs a medical team: usually an ENT, a feeding specialist, and sometimes a pediatric gastroenterologist or pulmonologist. Speech support sits alongside that care, never in place of it. And if your child's delay also shows up as repeated sounds, long pauses, or blocked words, online stuttering therapy can be done from your living room, which matters a lot when hospital visits already fill your calendar.
Let's start with the basics.
What is a laryngeal cleft?
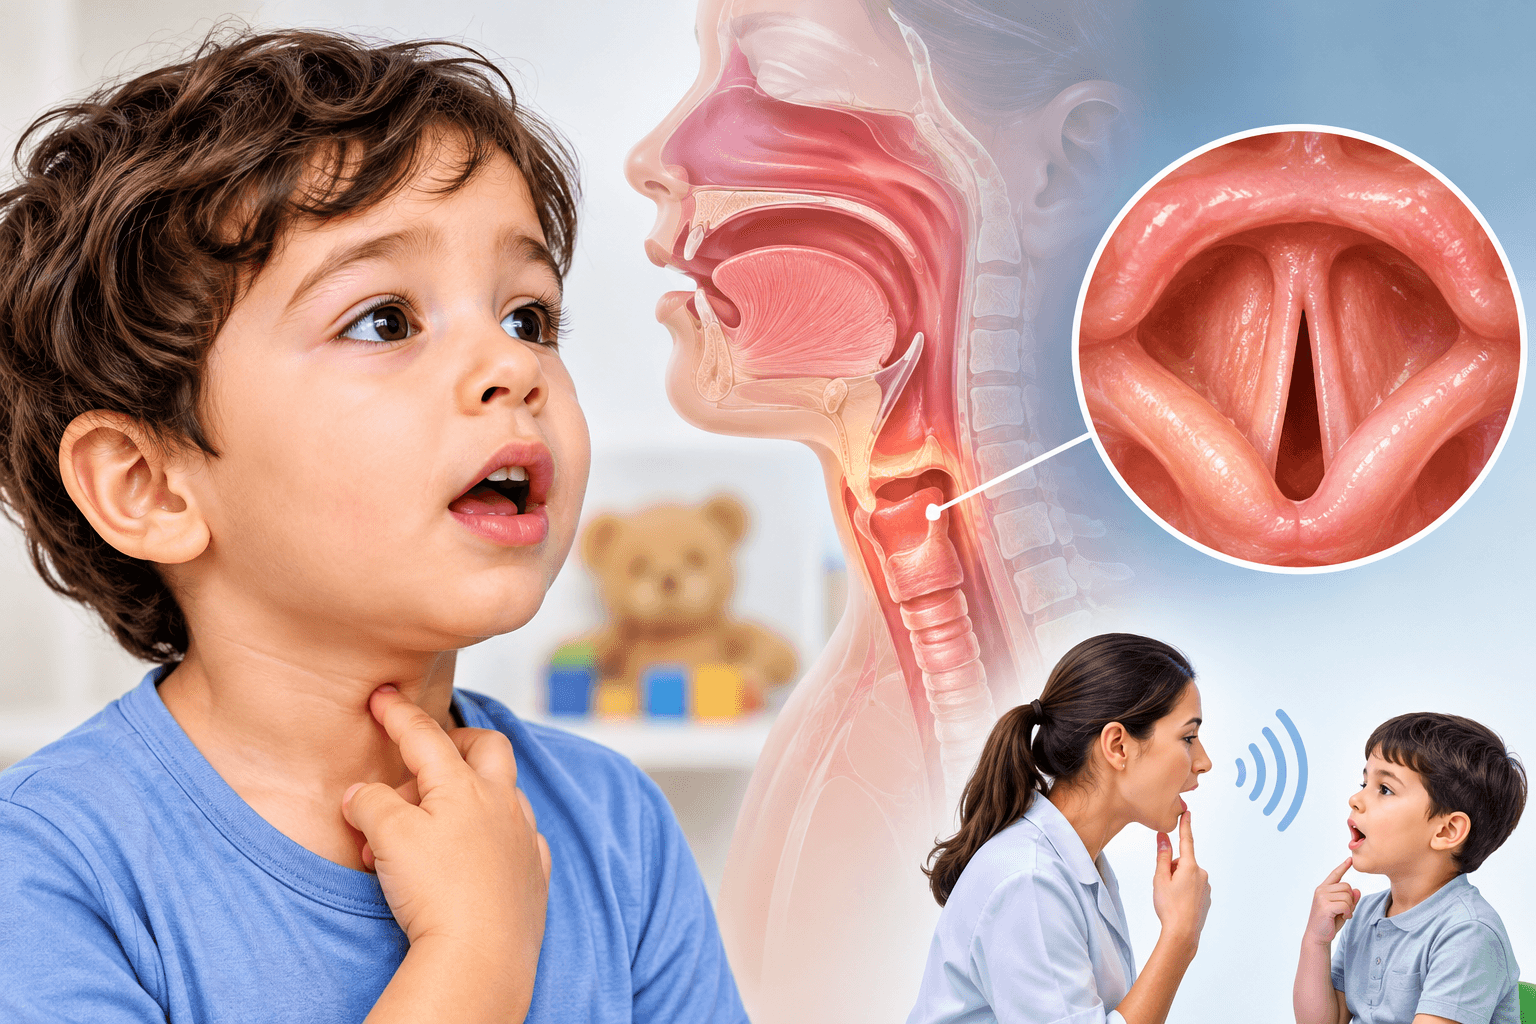
A laryngeal cleft is a rare condition some babies are born with. Normally, the voice box (larynx) and the food pipe (esophagus) are separated by a firm wall of tissue. In a laryngeal cleft, there's a gap in that wall. The size of the gap can vary a lot, from a small notch to a longer opening that reaches further down.
Because of that gap, milk or saliva can slip into the airway instead of going down to the stomach. Doctors call this aspiration. Sometimes it's loud and obvious, with coughing and choking. Sometimes it's silent, and the baby shows no reaction at all, which is one reason mild clefts get missed for months or even years.
Common signs include:
Coughing or choking during feeds
Noisy or wet-sounding breathing
A weak cry or a hoarse voice
Repeated chest infections
Very slow feeding, or refusing bottles and solids
Diagnosis usually involves a swallow study and, in many cases, a look at the airway under anesthesia. Treatment ranges from thickened feeds and careful positioning to a procedure that closes the gap. Your child's ENT will guide which path is right.
How laryngeal cleft can lead to speech delay
Here's where it gets interesting for parents. A laryngeal cleft doesn't directly "switch off" language. Most children with this condition understand words perfectly well. What it can do is get in the way of the building blocks that speech grows from.
1. The voice itself. The larynx is where your voice is made. If the area is irritated, scarred, or recovering from surgery, a child may sound hoarse, breathy, or quiet. Kids who sound unusual to themselves sometimes talk less, and kids who talk less practice less.
2. Oral-motor experience. Babies learn mouth control through sucking, chewing, and swallowing long before they say a word. When feeding is hard, tube-assisted, or limited, those early reps are fewer. That can show up later as clumsy tongue and lip movements.
3. Time away from play. Hospital stays, procedures, and frequent illness mean less everyday babble, back-and-forth games, and conversation. Language grows in ordinary moments, and those moments get interrupted.
4. Breath support. Speech runs on a steady, controlled breath. If airway problems have made breathing effortful, forming longer sentences can feel like a workout.
5. Hearing. Children with airway and feeding conditions can also have ear infections and fluid, which muffle sound. If a child can't hear clearly, speech develops slowly. A hearing test is always worth asking for.
None of this means your child won't catch up. It simply means the road to talking might have more detours, and that early support makes those detours shorter.
Speech delay and stuttering: are they the same thing?
No, but they often sit in the same room. A speech or language delay means a child is late reaching milestones: fewer words, simpler sentences, harder-to-understand speech. Stuttering is about the flow of speech: repeating sounds, stretching them, or getting stuck before a word comes out.
Children who are working hard to catch up on language sometimes begin stuttering as their sentences grow longer. It's a common stage, and many kids grow out of it. But if it lasts more than a few months, happens often, or comes with visible tension or frustration, it's worth getting looked at early. Waiting rarely helps, and early support is where the best results tend to happen.
What neuroscience tells us about speech
Talking feels effortless to adults, but it's one of the most demanding things the brain does. To say a single sentence, different brain areas have to plan the words, time the movements of the lips, tongue, jaw, and voice box, and listen to the result, all within a fraction of a second. It's a bit like an orchestra where every player must come in at exactly the right moment.
When a child has had early medical challenges, that orchestra may have had less rehearsal. And in children who stutter, research points to differences in how the brain's speech networks coordinate their timing. This is important, because it moves the conversation away from old myths. Stuttering isn't caused by bad parenting, nervousness, or a lack of effort. It's about how the brain times and sequences speech.
The encouraging part is neuroplasticity: the brain's ability to rewire itself through repeated, well-designed practice. Young brains are especially good at this. That's the idea behind the neuroscience method, which treats fluency as a brain-timing skill that can be trained, rather than a personality trait or something to be hidden or feared. If you'd like to see how it works in plain language, the page is worth a read.
Signs it's time to ask for help
Every child moves at their own pace, but these are good reasons to book an evaluation with a speech-language pathologist:
No single words by around 15 to 18 months
Fewer than about 50 words, or no two-word phrases, by 2 years
Speech that's hard for family members to understand after age 3
Hoarse, breathy, or very quiet voice that doesn't improve
Stuttering that continues for several months, or gets worse
Your child seems frustrated, avoids talking, or gets tense when speaking
Trust your gut. Parents of children with a laryngeal cleft have usually become experts in noticing small changes, and that instinct is valuable.
Simple ways to support speech at home
You don't need special equipment. Small habits, repeated daily, do a lot.
Narrate your day. "Now we're washing the cup. Splash, splash!" Short, simple, and full of sound.
Slow down. A calm pace gives your child time to think, and it models relaxed speech without you ever saying "slow down" to them.
Wait. After you ask a question, count to five in your head. Many kids need that pause to find the words.
Follow their lead. Talk about what they're already looking at or playing with.
Expand, don't correct. If they say "doggy go," you say "Yes, the doggy is going outside!"
Read together daily. Even five minutes helps. Point, name, repeat.
Play with sounds. Animal noises, blowing bubbles, and silly voices all build mouth and breath control.
Protect the feeling around talking. Never make your child repeat words or "try again" in a tense way. Speaking should feel safe.
Always check with your child's medical team before changing anything about feeding or mouth exercises, since swallowing safety comes first.
Working with the right team
Supporting a child with a laryngeal cleft and speech delay is a team effort. Your ENT manages the airway. A feeding therapist helps with safe swallowing. An audiologist checks hearing. A speech-language pathologist builds communication, and if stuttering is part of the picture, someone who understands fluency specifically makes a real difference.
That's also why consistency matters more than intensity. Short, regular sessions fit around medical appointments far better than long, exhausting ones, and children tend to learn best when they're rested and relaxed. Many families find that therapy from home removes a huge amount of stress, since there's no car seat, no waiting room, and no missed nap.
A final word for parents
It's easy to feel guilty when you see your child struggling to talk, especially after everything you've already carried. Please don't. A laryngeal cleft and the speech delay that can follow are not anyone's fault, and they're not the end of the story. With the right medical care, early support, and patient practice, many children make wonderful progress, and the brain keeps surprising us with how much it can change.
If you're noticing stuttering, long pauses, or blocked words alongside a speech delay, you don't have to figure it out alone. You can book a free stuttering consultation and talk through your child's situation with someone who understands both the science and the worry behind your questions.
Ready to Put This Into Practice?
Download the app and start practicing today
Reading is the first step. Real progress comes from consistent daily practice. Use StopStutter to build confidence and improve your speech every day.


