


ReviewOctober 27, 2026
Speech and Swallow Therapy: How Your Brain Relearns Talking and Swallowing
Most people don’t think about swallowing until it goes wrong. A sip of water that “goes down the wrong way,” a meal that suddenly takes twice as long, or a cough that shows up every time you eat. Speech works the same way. You never think about it until words get stuck, slur, or disappear. That’s why speech and swallow therapy sits under one roof: both skills depend on the same muscles, the same nerves, and, most importantly, the same brain.
If you landed here from a search like “how to stop stuttering,” you may wonder why a stuttering website is talking about swallowing. The connection is the point. Speaking and swallowing are both motor skills that the brain has to plan, time, and coordinate, and once you understand that, how to stop stuttering stops being a mystery about willpower and becomes a question about neural timing.
That’s also why therapy for these skills has moved away from “just try harder” advice. Whether someone is working on a stutter, a post-stroke swallowing problem, or slurred speech after a brain injury, a skilled clinician is really doing one thing: helping the brain build or rebuild a movement pattern. Today that can even happen from your living room, which is why online stuttering therapy has become a real option for people who can’t get to a clinic.
In this post, we’ll walk through what speech and swallow therapy actually is, what’s happening in the brain during both skills, who benefits, what a session looks like, and how neuroplasticity makes recovery possible.
What Is Speech and Swallow Therapy?
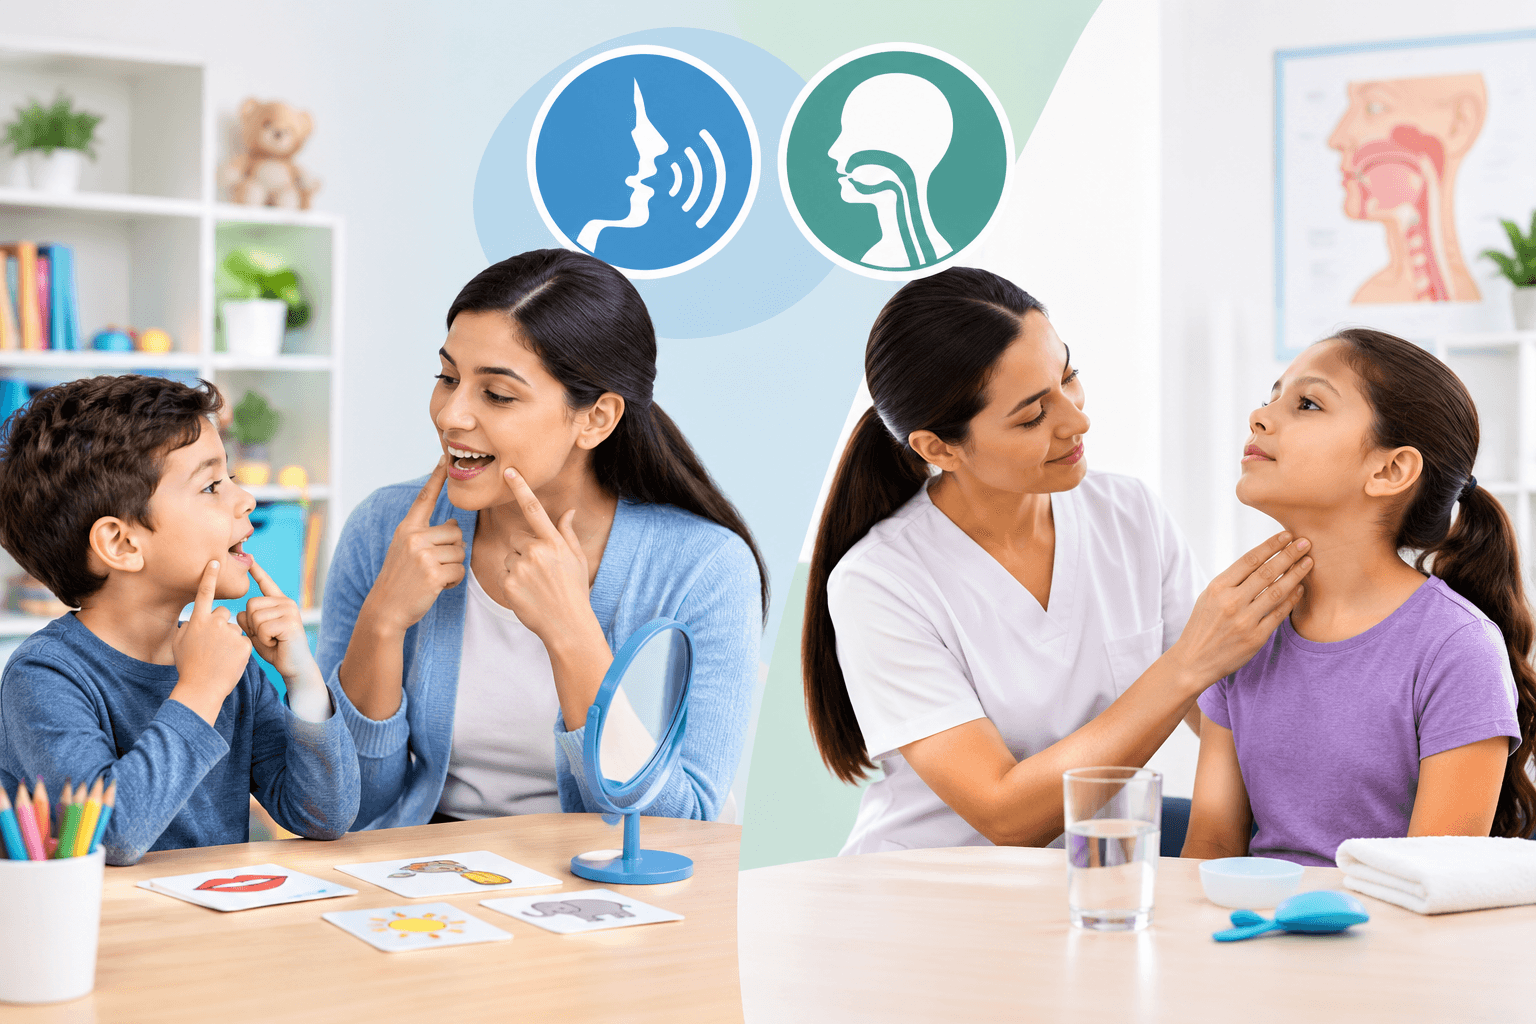
Speech and swallow therapy is treatment delivered by a speech-language pathologist (SLP) for problems with communication and for problems with eating, drinking, and swallowing, which is called dysphagia.
On the speech side, an SLP might work on articulation, voice, fluency (as in stuttering), language after stroke, or the slow, imprecise speech that comes with conditions like Parkinson’s disease. On the swallow side, the work focuses on how food, liquid, and saliva move from the mouth, through the throat, and into the esophagus without slipping into the airway.
The reason one professional covers both is anatomical. The lips, tongue, jaw, soft palate, and larynx do double duty. The same tongue that shapes an “s” sound also squeezes a bite of food toward the back of your throat. So when a nerve, muscle group, or brain region is affected, speech and swallowing often suffer together.
Why Speech and Swallowing Share the Same Brain Wiring
Here’s where it gets interesting.
Swallowing is partly automatic. A network in the brainstem, often described as a central pattern generator, runs the basic reflex sequence. But it doesn’t work alone. The motor cortex, the basal ganglia, the cerebellum, and several sensory areas all weigh in, especially when you swallow on purpose or when you’re eating something tricky like thin soup or dry crackers.
Speech leans on many of the same players. The motor cortex sends the commands, the basal ganglia help start and sequence movements, the cerebellum fine-tunes timing, and the brainstem nerves carry the signals out to the muscles of the face, mouth, and throat.
Notice the common thread: timing and sequencing. Both skills require dozens of muscles to fire in a precise order, within fractions of a second. Researchers studying stuttering have repeatedly pointed to differences in this kind of timing circuitry. In other words, a stutter and a swallowing problem can look very different on the surface while still living in the same neighborhood of the brain.
Who Needs Speech and Swallow Therapy?
A wide range of people benefit, and the causes are broader than most expect:
Stroke survivors, who may have weakness or poor coordination in the mouth and throat.
People with Parkinson’s disease or other neurological conditions, where movements become slower, smaller, or less coordinated.
Head and neck cancer patients, whose treatment can affect the tissues and nerves used for talking and swallowing.
Adults after a brain injury or concussion.
Older adults with gradual changes in swallowing strength.
Children with feeding difficulties or developmental speech problems.
People who stutter, whose main challenge is speech fluency rather than swallowing, but who often benefit from the same motor-learning principles.
If you or someone you love coughs or chokes during meals, has a wet or gurgly voice after swallowing, avoids certain foods, loses weight unexpectedly, or gets repeated chest infections, those are signs to get a swallowing evaluation promptly. Aspiration, when food or liquid enters the airway, can be silent, meaning there’s no obvious cough. That’s why an in-person assessment matters.
What Happens in a Session?
Every plan is individual, but sessions usually start with an evaluation. For swallowing, the clinician may watch you eat and drink different textures, check the strength and movement of your tongue, lips, and jaw, and listen to your voice quality. Sometimes they’ll recommend an instrumental test, such as a videofluoroscopic swallow study or a fiberoptic endoscopic evaluation, to see what’s happening inside the throat in real time.
Therapy itself often includes:
Strengthening exercises for the tongue, lips, and throat muscles.
Swallowing maneuvers like the effortful swallow or Mendelsohn maneuver, which change how the swallow is timed.
Posture adjustments, such as a chin tuck, that can protect the airway.
Texture and liquid modifications when needed for safety.
Speech drills that target clarity, loudness, rate, or fluency.
Breath and voice coordination work, since airflow supports both speaking and protecting the airway.
Your clinician decides which of these fit you. A technique that helps one person can be wrong for another, so it’s never wise to copy exercises you find online without guidance.
Neuroplasticity: The Reason Therapy Works
Everything above rests on one idea: the brain can change. This is neuroplasticity, and it’s the engine behind both speech and swallow therapy.
When you repeat a movement with focus and feedback, the connections between neurons involved in that movement get stronger and more efficient. When a stroke damages one area, neighboring or related regions can sometimes take on part of the job, but they usually need structured, repeated practice to do it.
A few principles researchers highlight again and again:
Repetition matters. Skills are built through lots of practice, not a handful of attempts.
Intensity matters. Practice that’s challenging enough to require effort drives more change than going through the motions.
Specificity matters. To improve swallowing, you practice swallowing-related tasks. To improve speech, you practice speech.
Timing matters. In many conditions, earlier intervention gives the brain more room to adapt.
Feedback matters. Knowing what you did right or wrong helps the brain refine the pattern.
None of this is magic, and results vary depending on the cause, the severity, and the person’s overall health. But it explains why therapy is built around structured practice and not just reassurance.
What This Teaches Us About Speaking Fluently
Now back to where we started. The same logic applies to stuttering. A stutter isn’t a character flaw, a lack of confidence, or a sign that someone isn’t trying hard enough. It reflects how the brain times and sequences speech movements, and that pattern can be shaped with the right practice.
Many people who stutter spend years trying to hide it, avoid words, or push through tension. A brain-based approach flips that. Instead of fighting the moment of a block, you learn to work with the underlying system: calming the threat response that tightens the muscles, improving timing, and building new, smoother speech patterns through repetition.
If that sounds like the kind of change you’ve been hoping for, you don’t have to figure it out alone. You can book a free stuttering consultation to talk through your own speech pattern and see what a brain-based plan could look like for you. It’s a low-pressure way to get your questions answered before you decide anything.
How to Get the Most Out of Therapy
Whether you’re working on speech, swallowing, or both, a few habits make a real difference:
Practice a little every day. Short, regular sessions beat one long weekly marathon. The brain consolidates skills during the time between practices.
Be patient with plateaus. Progress rarely looks like a straight line. Some weeks feel flat, and then something clicks.
Stay safe during meals. If you have a swallowing problem, follow your clinician’s guidance on food textures, posture, and pacing. Eating slowly, sitting upright, and avoiding distractions all reduce risk.
Tell your clinician what’s really going on. Fear of choking, embarrassment when talking, or skipping meals with friends are all important clues. They shape the plan.
Involve your support system. Family members can help you remember strategies, notice changes, and cheer you on.
Know when to seek urgent help. Trouble breathing, repeated choking, fever after eating, or sudden changes in speech or swallowing need immediate medical attention.
Final Thoughts
Speech and swallow therapy works because it respects how the brain actually learns. Talking and swallowing look like completely different activities, but they draw on shared circuitry and the same principle: the brain can strengthen what it practices. With the right assessment, a personalized plan, and consistent effort, many people regain confidence in their voice and comfort at the dinner table.
If your own challenge is stuttering, that same brain-first thinking is where lasting change begins. Take a closer look at the science behind neuroscience stuttering to see how rewiring speech patterns works, and why so many people feel it finally explains what years of “just slow down” advice never could.
Ready to Put This Into Practice?
Download the app and start practicing today
Reading is the first step. Real progress comes from consistent daily practice. Use StopStutter to build confidence and improve your speech every day.


