


ReviewOctober 28, 2026
Speech Therapy for Dementia: How the Brain Keeps Communicating
There’s a moment many families remember. Dad starts a sentence he has said a thousand times, and halfway through, the word simply isn’t there. He pauses, searches, and either gives up or substitutes something close. Everyone in the room pretends it didn’t happen.
If you have seen that moment, you already know that dementia is not only about memory. It changes how a person talks, understands, and connects. That is why speech therapy for dementia has become one of the most practical forms of support available, and why more families are asking about it.
At StopStutter, our work centers on how the brain produces speech. People usually find us while searching for overcome stuttering, but the brain systems behind fluent speech are the same ones that dementia puts under pressure. Understanding those systems makes the whole topic less frightening.
We deliver online stuttering therapy rather than dementia care, so this guide is educational. It is not a replacement for your neurologist or a speech-language pathologist who knows your family member’s diagnosis. What we can offer is a clear, honest look at what is happening in the brain and what good communication support looks like.
What dementia does to speech and language
Dementia is an umbrella term. Alzheimer’s disease, vascular dementia, Lewy body dementia, and frontotemporal dementia each affect different brain regions, so they affect communication differently.
In Alzheimer’s, word-finding trouble often shows up early. The person knows what a key is for but can’t pull up the word “key.” In frontotemporal dementia, language itself can be the first thing to change. Some people lose the meaning of words, while others start speaking in short, effortful, halting phrases. Vascular dementia can make speech slow or slurred, depending on where the damage sits.
The common thread is that speech is one of the most demanding things the brain does. It needs memory, attention, motor planning, and emotional regulation all working together within a fraction of a second. When any one of those starts to slip, talking becomes harder.
The neuroscience behind speech therapy for dementia
Here is the part that surprises people. Speech is not stored in one place. It runs through a network that includes frontal regions for planning, temporal regions for meaning, and deeper structures like the basal ganglia that handle timing and rhythm.
Dementia damages parts of that network, but rarely all of it at once. That matters because brains are built to reroute. Neuroplasticity, the brain’s ability to strengthen connections that are used and form new routes around damaged ones, doesn’t switch off with age or diagnosis. It slows down and becomes less flexible, but it remains.
This is the principle that good speech therapy for dementia is built on. A therapist is not trying to restore what’s lost. They are looking for the pathways that still work and giving them regular, meaningful practice. Think of it as keeping the lights on in the rooms that are still occupied.
What speech therapy for dementia actually looks like
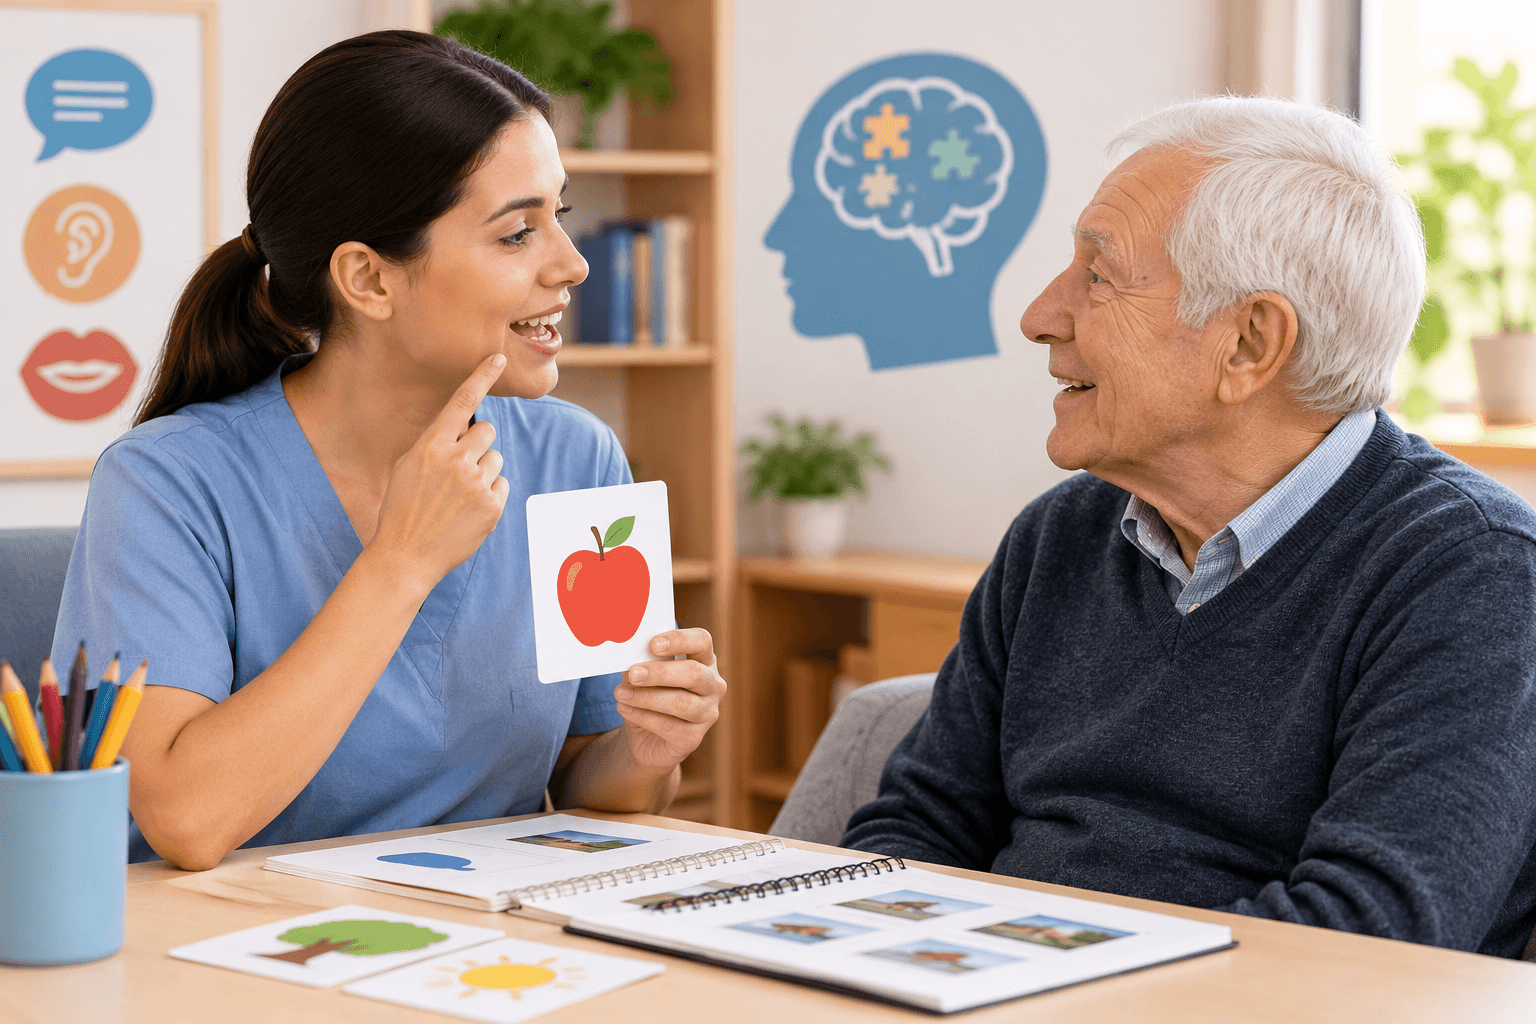
Families often picture flashcards and drills. Modern practice is much warmer and more personal than that. A speech-language pathologist usually starts with a thorough assessment of what the person can still do well, which words they reach for, and where frustration begins.
From there, therapy tends to include a few core strands:
Word retrieval strategies. Cueing with the first sound, describing an object when the name escapes, or using gestures to bridge the gap.
Memory aids that support speech. Photo books, personalized word lists, and daily routine boards that give the brain external anchors.
Conversation training for the whole family. Often the biggest wins come from teaching the people around the person with dementia to communicate differently.
Swallowing support. Speech-language pathologists also assess and manage swallowing, which can become difficult as dementia progresses.
Sessions are usually short. Long sessions tire the brain and raise anxiety, and anxiety is one of the fastest ways to lose words.
Why stress steals words (and why it matters)
This is where our experience with stuttering becomes useful. People who stutter know that tension makes speech worse. The brain’s threat response, driven by the amygdala, floods the system with alertness, and the fine timing that speech needs falls apart.
The same thing happens in dementia. A person who feels tested, rushed, or corrected will have more word-finding trouble, not less. Their brain spends resources on feeling unsafe instead of finding the word.
That is why a calm pace matters so much. Pauses are not failures, and silence gives the brain time to run its search. Many families are amazed that the word they were waiting for arrives on its own when nobody jumps in too soon.
Practical ways to communicate at home
You don’t need a clinic to start using what speech therapy teaches. A few habits make a real difference:
Ask one question at a time. Avoid stacking two or three in a single breath.
Offer choices instead of open questions. “Would you like tea or coffee?” is easier than “What would you like to drink?”
Wait longer than feels natural. Count to ten in your head before filling the gap.
Reduce background noise. A running television makes it much harder for a damaged language network to focus.
Don’t correct. If the meaning is clear, let the wrong word go.
Use the whole person. Touch, facial expression, and tone carry meaning long after vocabulary fades.
None of this is complicated. But it works because it matches how the brain behaves under strain.
Music, rhythm, and the parts of the brain that stay strong
One of the most hopeful findings in this field concerns rhythm. Many people with dementia can sing the lyrics to a song they loved at twenty, even when they struggle to hold a conversation.
Singing and speaking use overlapping but distinct pathways, and musical memory is stored more widely across the brain. Speech therapists use this by weaving melody, humming, and rhythmic tapping into sessions. It can help with word access, and just as importantly, it brings back moments of joy and connection.
Stuttering offers a parallel. Many people who stutter speak fluently when singing or speaking in time with a beat, because rhythm recruits timing circuits that bypass the usual bottleneck. The brain has back doors, and good therapy learns where they are.
When to seek help
Early is better. Speech therapy for dementia works best when it starts while the person can still take part in setting goals, learning strategies, and building routines they will lean on later.
Signs worth raising with a doctor include frequent word-finding pauses, trouble following conversations in groups, repeating the same questions, losing the thread mid-sentence, or new slurring or hesitation in speech. These can have many causes, so an evaluation matters before assuming anything.
It is also worth saying that sudden changes in speech, such as new stuttering-like repetitions or blocks appearing in an adult with no history of stuttering, can be a sign of a neurological change. That deserves prompt medical attention, not a wait-and-see approach.
Looking after the caregiver, too
Caregivers rarely hear this: your communication matters as much as your loved one’s. Exhausted, worried people speak faster, ask more questions, and finish sentences without meaning to. All of that is human, and all of it can make the person with dementia feel more rushed.
A speech-language pathologist can coach you directly. Many families say the biggest shift wasn’t a change in their relative’s speech at all. It was feeling less helpless themselves.
If you’re carrying the weight of a speech or communication concern in your family, whether it’s dementia, a stutter, or something you can’t name yet, you don’t have to figure out the first step alone. You can book a free stuttering consultation with our team to talk through what you’re seeing and get pointed in a sensible direction, even if the answer is that you need a different kind of specialist.
What the research direction tells us
Researchers continue to study how language networks change in different dementias and which therapy approaches hold up best. The honest picture is that speech therapy for dementia is not a cure and cannot stop the underlying disease. What it can do is help people communicate with more confidence, keep their social world open longer, and reduce frustration on both sides of the conversation.
Those gains are not small. Being able to say “I’m cold,” “I love you,” or “I don’t want that” is the difference between being a participant in your own life and being talked about from across the room.
Final thoughts
Dementia changes the way a person speaks, but it doesn’t erase the person who is speaking. The brain keeps looking for routes, and with patient listening, thoughtful strategies, and the right professional support, many of those routes stay open far longer than families expect.
If you’re starting this journey, begin with a proper assessment, slow your own pace down, and protect the moments of connection that still come easily. And if you want to understand how the brain builds and loses fluent speech in more depth, our guide to neuroscience stuttering explains the same systems from the ground up. It’s a good place to start making sense of what you are seeing.
Ready to Put This Into Practice?
Download the app and start practicing today
Reading is the first step. Real progress comes from consistent daily practice. Use StopStutter to build confidence and improve your speech every day.


