


ReviewOctober 8, 2026
Speech Therapy After Stroke: Exercises, Recovery Time and What Works at Home
Speech therapy after stroke is a guided program with a speech-language pathologist that helps survivors speak clearly, find words, follow conversations and swallow safely again. It often starts in hospital within the first few days, and the fastest gains usually show up in the first three to six months, though plenty of people keep improving long after that. Practice at home fills the gaps between clinic visits. If a stroke has left someone repeating sounds or getting stuck on words, the team at Stop Stutter can help with the fluency side of recovery.
At StopStutter, our daily work is helping people speak with more ease, so we understand how personal it feels when words won’t come. We aren’t a stroke rehabilitation hospital, and nothing here replaces your neurologist or speech-language pathologist. What we can do is explain the process in plain language, share habits that fit alongside medical care, and show where fluency work and stroke recovery overlap.
Stroke can affect speech in more than one way. Some people lose words, some slur, and some start repeating sounds in a way that looks a lot like stuttering. Once the medical side is stable, many families also explore online stuttering therapy for the fluency and confidence side of recovery, because practice can happen at home, at a pace that suits a tired brain.
Stroke Speech Therapy: What Changes in the Brain and Why It Works
A stroke cuts off blood flow to part of the brain, and the cells in that area get damaged. If the damage sits in the regions that handle language or mouth movement, speech changes. The encouraging part is neuroplasticity. The brain can form new connections and hand old jobs to healthy neighbouring areas. Therapy gives it the repetition it needs to do that. Progress tends to be fastest in the first few months, but many survivors keep gaining skills long after that.
Speech Therapy After Stroke: Common Problems You May See
Not every survivor has the same difficulty, which is why an assessment comes first. These are the patterns therapists look for:
Aphasia: trouble finding, forming or understanding words. A person may know exactly what they want to say and still reach for the wrong word, which is often more frustrating than silence.
Apraxia of speech: the brain struggles to plan the mouth movements for speech, so sounds come out effortful, inconsistent or in the wrong order even though the muscles aren’t weak.
Dysarthria: weak or slow muscles around the mouth, tongue and lips, which can make speech slurred, quiet or breathy.
Acquired stuttering: new repetitions, blocks or prolonged sounds that appear after a neurological event, often with visible tension.
Swallowing difficulty: it often travels alongside speech problems, so the same therapist usually checks both.
After Stroke Can’t Speak? Understanding No Speech After a Stroke
Hearing “my father had a stroke and now he can’t speak” is more common than people realise. Having no speech after a stroke doesn’t always mean the person has lost their thoughts. In many cases understanding stays much stronger than talking. Gestures, drawing, writing, picture boards and even singing can open a door when ordinary speech stays shut. Talk to your loved one as the capable adult they are, include them in decisions, and let silence be part of the conversation instead of rushing to fill it.
Speech Therapy Following Stroke: What to Expect in the First Months
Early, regular practice matters. Short sessions several times a day usually beat one long, exhausting session, because tired brains learn poorly. Your therapist will set goals around what matters in real life, such as asking for water, answering the phone or chatting with grandchildren.
Speech Therapy for Aphasia After Stroke
For aphasia, therapy often combines naming tasks, sentence building, comprehension work, reading and writing. Some approaches use rhythm and melody to unlock words that normal speech can’t reach. The best plan is built around the person’s own vocabulary, such as their hobbies, family names and work terms, because familiar words come back more readily than random ones.
Speech Exercises After Stroke Worth Asking Your Therapist About
Never copy a routine from the internet without checking, since the right exercise depends on the type of difficulty. These are good conversation starters with your care team:
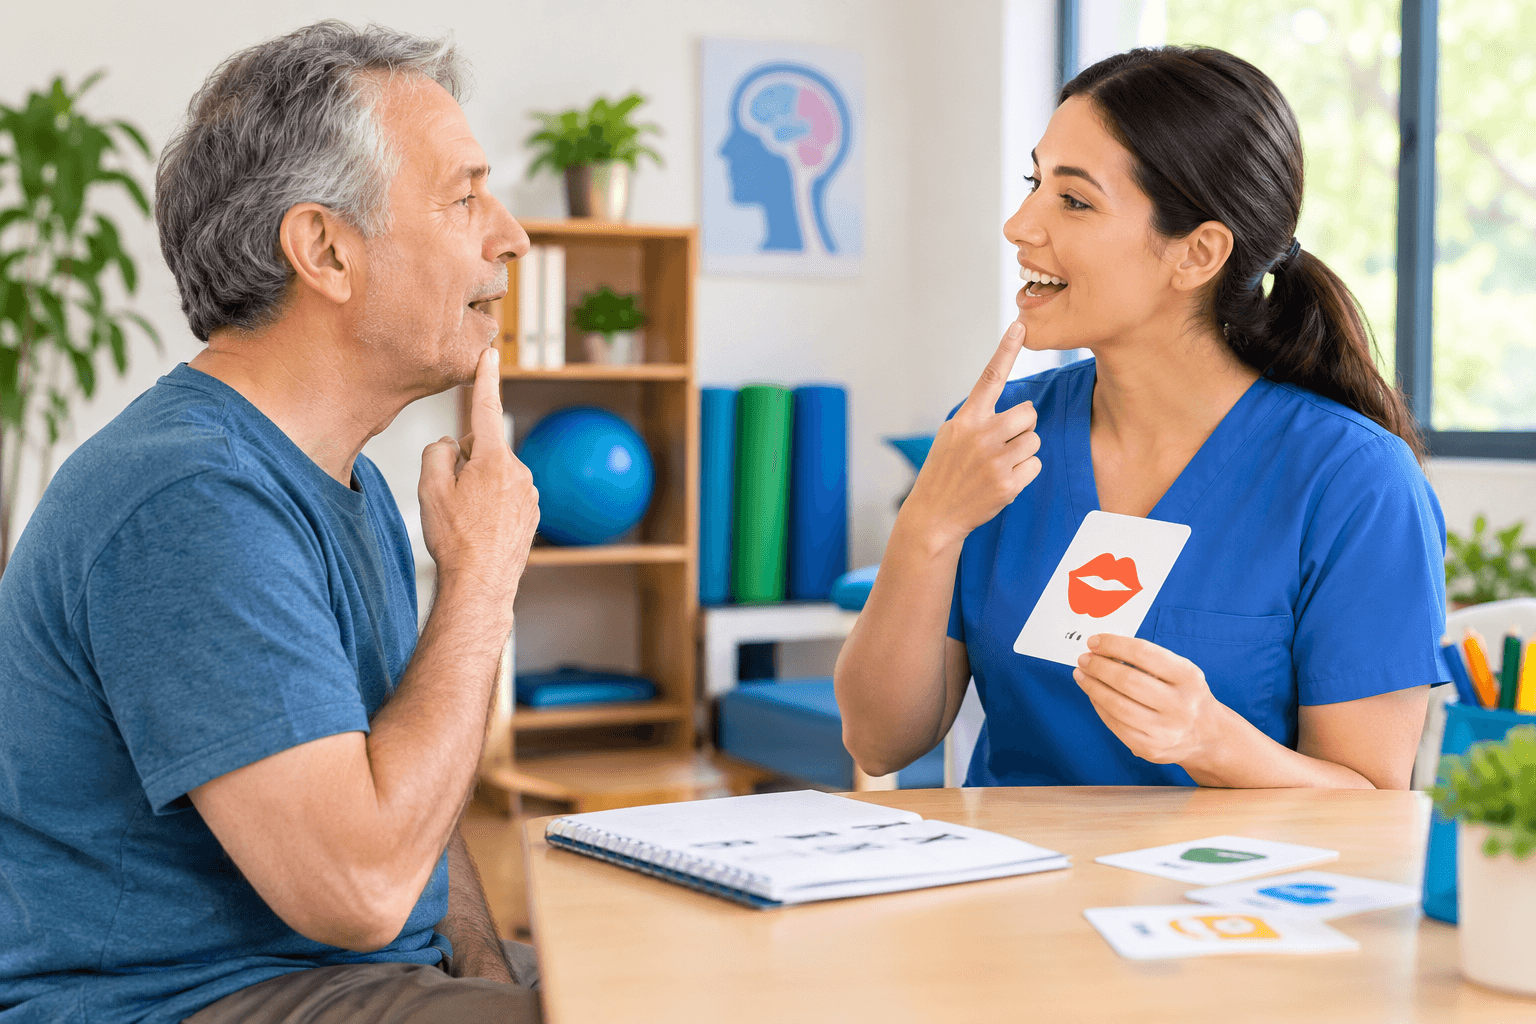
Slow mouth warm-ups: gentle lip, tongue and jaw movements done in front of a mirror help the person see what the mouth is doing and notice tiny improvements that are easy to miss.
Automatic speech practice: counting, naming the days of the week or reciting a familiar prayer or song often comes more easily and builds confidence before moving on to harder, more spontaneous words.
Breath and phrasing: speaking one short phrase per breath reduces rushing and strain. Pacing ideas like this overlap with the top 7 stuttering therapy techniques that actually work, many of which therapists adapt for people with effortful speech.
Reading aloud: a short paragraph read slowly each day trains accuracy, and recording it lets the person hear progress over weeks.
Stroke Speech Therapy at Home: Simple Daily Practice That Fits Real Life
Clinic sessions are only a few hours a week. Real recovery is built in the hours between, so home practice matters. Keep it relaxed, keep it short, and stop before frustration builds. Ten to fifteen minutes done kindly is worth more than an hour done with tears.
Speech Therapy Activities for Stroke Patients You Can Try Today
Kitchen naming game: pick up everyday objects and name them together, then move on to describing what they do. Real objects tie words to memory far better than flashcards on a screen.
Picture description: choose a family photo and let the person describe who is there and what is happening, using single words, gestures or short sentences, whatever they manage that day.
Role-play routines: practise the exact sentences needed for ordering tea, greeting a neighbour or calling a pharmacy. Rehearsing real situations lowers fear when the moment arrives.
Music and singing: old songs often survive when ordinary speech doesn’t, and singing a line can warm up the voice and lift mood at the same time.
Voice notes: record a short message each week to a friend and play the old ones back later. Progress feels invisible day to day, but it becomes obvious across a month.
It also helps to know whether understanding or expressing is the harder part, because activities differ. Our explainer on receptive vs expressive language makes that difference easy to see.
Stroke and Speech Pathology: What Happens in the First Session
Background questions: The therapist asks when the stroke happened, how speech has changed and what the person most wants to say again.
Simple screening tasks: Expect things like naming pictures, repeating words, following short instructions and reading a line aloud.
A swallowing check: This is often done in the same visit, because speech and swallowing use many of the same muscles.
Two or three real-life goals: Examples are ordering tea, answering the phone or chatting with a grandchild.
A starter home plan: A few short tasks, plus guidance for family on how to help without taking over.
Speech Therapy Following Stroke: What Recovery Can Look Like Over Time
First weeks: The focus is safe swallowing, yes and no answers and simple ways to communicate, like gestures or picture boards.
Months one to three: This is usually the most active rebuilding phase, with naming work, sentence practice and daily short sessions.
After three months: Gains often slow down but do not stop. Therapy moves toward real conversations, group practice and confidence.
Pace differs for everyone: A bad day is normal and does not mean going backwards.
How to Help a Stroke Patient Talk Again
Families often want to do everything, and that love is valuable. The trick is to support without taking over. Many survivors say the hardest part isn’t the speech itself, it’s feeling like people have stopped waiting for them.
Small Habits That Make a Big Difference
Give extra time: wait a full ten seconds before helping. That pause often feels awkward to you but gives the brain just enough room to finish the search.
Cut the background noise: turn off the television and move to a quiet room, because competing sounds make word-finding and understanding noticeably harder.
Ask simple questions: offer yes or no questions or two clear choices when energy is low, and open questions when the person is fresh.
Celebrate effort, not accuracy: praise the attempt, not only the perfect word, so the person keeps trying instead of going quiet to avoid mistakes.
When Speech Feels Stuck or Repeats
If new repetitions or blocks appear, learning the vocabulary helps everyone stay calm. Our guide to the core behaviors of stuttering explains what repetitions, prolongations and tension look like, and our piece on how to speak clearly shares pacing and articulation habits that many people find useful. If the voice sounds strained or gives out by evening, why voice cracks happen is worth a read. And if little ones at home start copying a grandparent’s repeated sounds, our article on 2-year-old stuttering can reassure you about what’s normal in children.
Speech Therapy for Stroke Recovery: What the Process Really Looks Like
Most families only hear the words “speech therapy” and have no idea what the weeks ahead involve. Here is a plain version of how stroke speech therapy usually unfolds.
Speech Language Therapy for Stroke: Who Is Involved
A speech-language pathologist leads the plan and tests speech, language, reading and swallowing.
A neurologist or doctor handles the medical side and refers you for therapy.
Family members learn simple ways to help at home without taking over.
Occupational therapists and physiotherapists often work alongside, since movement and speech improve together.
Stroke Speech Recovery Time: What Most Survivors Notice
Weeks one to four: safe swallowing, yes and no answers, and basic ways to communicate.
Months one to three: the busiest rebuilding stage, with naming work and short sentences.
Months three to six: speech often becomes clearer and conversations feel less tiring.
After six months: progress slows but keeps going, especially with regular practice.
Speech Therapy for Stroke Victims: Signs It Is Time to Ask for Help
Words are slurred, quiet or hard for others to follow.
The person knows what they want to say but cannot find the word.
Sentences come out jumbled or in the wrong order.
New repeated sounds or blocks have appeared since the stroke.
Talking leaves the person exhausted or unwilling to join conversations.
Stroke Speech Therapy Exercises to Bring Up at Your Next Session
Mirror work for lips, tongue and jaw, done slowly.
Counting days of the week or familiar songs to build easy, automatic speech.
One short phrase per breath to cut down rushing and strain.
A daily read-aloud paragraph, recorded so progress is easy to hear.
Frequently Asked Questions
What are the best speech therapy exercises after a stroke?
The best exercises depend on the type of speech difficulty, so a therapist should choose them after an assessment. Common starting points include slow lip and tongue movements, counting or reciting familiar songs, naming everyday objects and reading a short paragraph aloud. Short sessions several times a day usually work better than one long, tiring one.
Is speech therapy post stroke only for people who can’t talk?
No, it helps with much more than silence. A therapist also works on slurred speech, finding the right word, understanding conversations, reading, writing and swallowing. Even people who speak fairly well often benefit, because small difficulties can still make daily conversations tiring and frustrating.
How often should stroke patients practise speech therapy at home?
Most people do best with 10 to 15 minutes of relaxed practice, a few times a day. Your therapist may suggest a different schedule based on energy levels and the type of difficulty. It is better to stop while the session still feels manageable than to push until frustration sets in.
What can family members do to help with speech therapy for stroke patients?
Give the person plenty of time to finish their words, and wait before stepping in to help. Turn off background noise, ask simple questions and praise the effort, not just the perfect answer. Family can also learn the home exercises from the therapist so that practice feels natural in everyday routines.
Can speech therapy help if the stroke happened months or years ago?
Yes, in many cases it can. The brain keeps its ability to adapt long after the early recovery period, and many survivors continue to gain skills with regular practice. Progress may be slower than in the first months, so a therapist can set smaller, realistic goals and adjust them over time.
Speech Therapy Stroke Rehabilitation: Why Brain-Based Practice Works
Speech depends on timing, attention, emotion and muscle control all working together, and a stroke can disturb any of them. That’s why calm, repeated, brain-friendly practice beats pushing hard. At StopStutter, our neuroscience method is built on this idea: reduce tension, build awareness and practise in small steps so the brain learns new patterns without feeling threatened. Its principles of pacing, confidence and gentle repetition fit well alongside the medical therapy your speech-language pathologist provides.
Your Next Step in Stroke Speech Recovery
Speech therapy for stroke patients works best when patience, expert guidance and daily practice come together, and no one has to do it alone. If you’d like to talk through fluency, confidence or speech concerns, you can book a free consultation with our team and take a calm first step.
Ready to Put This Into Practice?
Download the app and start practicing today
Reading is the first step. Real progress comes from consistent daily practice. Use StopStutter to build confidence and improve your speech every day.


