


ReviewSeptember 17, 2026
Does Tongue Tie Affect Speech
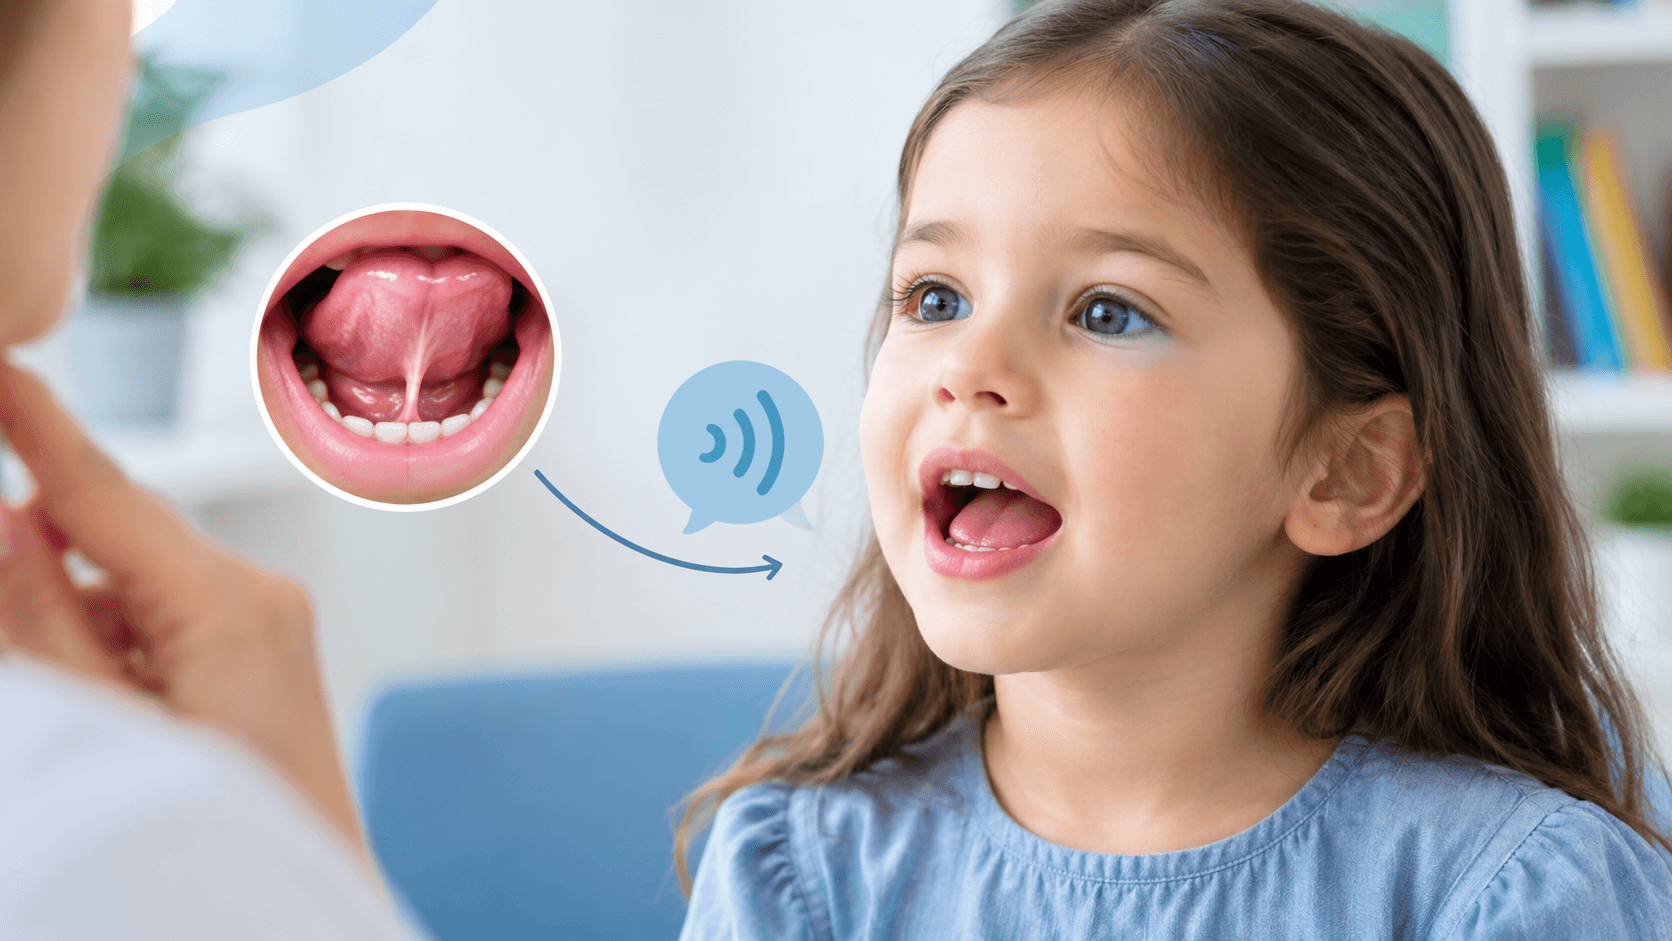
Does tongue tie affect speech? Short answer, yes it can, but only sometimes and rarely in the way people expect. Tongue tie (the clinical name is ankyloglossia) restricts how far the tongue can move, which can mess with sounds like t, d, l, r, s, and z. What it won't do is cause stuttering, though plenty of parents worry about that link. Sorting out whether you're dealing with a physical restriction or a brain-based speech condition changes everything about treatment, including whether a proven neuroscience stuttering method might be the better route to lifelong fluency.
Can Tongue Tie Cause Speech Delay?
Some kids with tongue tie do talk later than their peers, but pinning the delay on tongue tie alone is usually a mistake.
A tight frenulum can restrict the movements babies use to form their first sounds
Early feeding struggles sometimes leave oral muscles underdeveloped
Plenty of tongue-tied kids hit every milestone right on time
Genuine delay is almost always tied to several factors at once, not just anatomy
How much a child is spoken to and read to matters as much as physical structure
Before jumping to surgery, get a pediatric SLP to run a proper functional assessment. Too many kids end up on the table for a delay that had nothing to do with their frenulum. More on signs your child needs speech therapy.
Do Tongue Ties Cause Speech Problems in Adults?
Adults with untreated tongue tie can absolutely run into articulation trouble, though most people build workarounds without realizing it.
Talking fast gets tricky, especially in long conversations
Certain consonants come out slurred or soft
The jaw and tongue tire quickly during extended talking
Background noise makes clarity harder than it should be
Projecting the voice or holding volume takes real effort
Here's what adult tongue tie will not do: cause you to stutter. Blocks, repetitions, sound prolongations, that stuck feeling when you try to push a word out, none of that comes from your frenulum. It's neurological, and anyone Googling how to stop stuttering needs to look somewhere other than surgery.
Tongue Tie Speech Therapy: What Actually Helps
Speech therapy for tongue tie usually shows up in one of two contexts: as follow-up after a frenectomy, or as the sole treatment when the tie is mild enough that surgery isn't on the table.
Post-release work builds strength and control in the freed tongue
Compensatory therapy teaches the tongue to get around what it still can't do
Oral motor drills sharpen elevation, side-to-side movement, and precision
Articulation practice zeros in on the sounds giving the most trouble
Myofunctional therapy resets how the tongue rests and how swallowing works
None of this helps someone who stutters. Stuttering needs online stuttering therapy built on how the brain plans speech, not exercises that make the tongue stronger.
Does Posterior Tongue Tie Affect Speech Differently?
Posterior ties sit further back and hide under the tongue, which is why they get missed so often during quick exams.
They tend to show up as subtle issues, mostly in harder words
Diagnosis usually comes later than for anterior ties
Speech can sound slightly muffled or unfocused without an obvious cause
Getting the right call means finding a clinician who works specifically with oral restrictions
Lip ties and infant feeding problems often travel with them
That said, not every posterior tie needs fixing. Many cause no problems at all. The judgment has to come from a functional exam, not from a quick look under the tongue.
Mild Tongue Tie and Speech: Is Treatment Even Necessary?
Whether a mild tongue tie needs any intervention is probably the question pediatricians hear most often, and there's no one-size answer.
Mild cases often loosen naturally as the mouth grows
Speech clarity commonly develops fine with no procedure at all
Surgery makes sense when function is clearly getting in the way, not before
Watching and waiting works well for anything borderline
Getting a second opinion is smart whenever a mild case gets flagged for surgery
There's a real trend toward overtreating mild ties right now, and it's worth pushing back on. Focus on what the child can actually do, not what the tongue looks like when it's lifted.
Tongue Tie vs Stuttering: The Difference That Changes Everything
This is where most confusion starts. Tongue tie is a physical thing. Stuttering happens in the brain.
Tongue tie means the frenulum is holding the tongue back from moving freely
Stuttering means the brain's speech planning gets interrupted
With tongue tie, sounds come out distorted but they keep coming
With stuttering, speech itself stalls, repeats, or gets blocked
Surgery and oral exercises fix tongue tie
Only neurological work fixes stuttering
Picture a child saying "wed" when they mean "red." Now picture a child saying "r-r-r-red." Two completely different problems, and mixing them up costs years of misdirected effort. More on stammer vs stutter.
Tongue Tie Speech Therapy Exercises for Home Practice
Working with an SLP, families can build tongue mobility with a handful of exercises done consistently over weeks.
Tongue push-ups: press the tongue against the roof of the mouth for a slow five count
Tongue stretches: reach toward the nose, then the chin, then each cheek
Cheerio game: hold a cheerio on the roof of the mouth with the tongue tip
Suction hold: suction the tongue up and open and close the jaw
Sound repetition: say la, ta, da, na slowly and clearly in short sets
Bubble blowing: helps with breath control and general oral coordination
For anyone stuck on stuttering, these do nothing. Real fluency starts by changing how the brain plans and produces speech, and that's a different kind of work entirely.
Speech Problems Due to Tongue Tie vs Other Speech Impediments
Speech impediments come in more flavors than people realize, and the right treatment depends on figuring out which kind you're actually dealing with.
Articulation disorder: specific sounds come out wrong
Fluency disorder or stuttering: the rhythm of speech keeps breaking
Voice disorder: pitch, loudness, or vocal quality is off
Phonological disorder: whole patterns of sounds get swapped or dropped
Motor speech disorder: the brain struggles to plan or execute movements
Tongue tie mostly fits under articulation. Stuttering is a fluency problem, and no scalpel is going to change that.
Speech Therapy After Tongue Tie Release: What Comes Next
A frenectomy on its own rarely erases speech habits built up over years, which is why the follow-up therapy is arguably more important than the procedure itself.
Wound stretches and basic aftercare kick in within a day
Articulation work usually begins one to two weeks post-op
Real functional change often takes three to six months of steady practice
Adults and older kids need noticeably longer to retrain than toddlers do
Regular check-ins keep the therapy pointed at what's actually improving
The number one reason parents feel a release "didn't work" is that they skipped the therapy piece. Surgery just opens the door; therapy walks the tongue through it.
How to Tell If Tongue Tie Is Affecting Your Toddler's Speech
For kids between two and five, keep an eye out for these patterns, keeping in mind that missing a sound here and there is completely normal.
Trouble with t, d, l, r, s, or z sounds that sticks around past age four
Can't easily lick their lips or wiggle the tongue side to side
A history of feeding trouble that carried into how they now talk
Speech noticeably harder to understand than what other kids their age produce
A heart-shape or notch appears at the tip when they lift the tongue
If what you're actually seeing is your child getting stuck on words, repeating sounds, or freezing mid-sentence, that's disfluency, not tongue tie. Early help matters for either one, but the help has to match what's actually going on. See our guides on 2-year-old stuttering and stuttering in 4-year-olds.
Why the Neuroscience Method Works Where Traditional Therapy Falls Short
Once it's clear the issue is stuttering rather than tongue tie, conventional therapy often disappoints because it treats what shows up on the surface instead of what's happening underneath. The World Stop Stuttering Association took a different route with its neuroscience method.
It targets the brain circuits behind speech planning, not the tongue itself
Neuroplasticity is used to permanently rewrite disfluent patterns
Mental and mindset work runs alongside the practical fluency skills
Changes stick rather than fading the way trained control usually does
Thousands of former stutterers stand behind the results
Everything runs online, so the location of the expert doesn't matter
Plenty of people spent years convinced their tongue was the problem, only to find real fluency once the focus shifted to the brain. That shift, from anatomy-first to neurology-first, is what makes the difference. Read one such journey in rewiring the brain.
Frequently Asked Questions
How to tell if tongue tie is affecting speech?
Watch for ongoing trouble with tongue-tip sounds like t, d, l, and r after age four, alongside limited tongue movement and an inability to lift the tongue up to the palate. A pediatric SLP is the right person to confirm whether tongue tie is really behind what you're seeing.
What happens if you don't fix a tongue tie?
Most people who go untreated do fine. Possible downsides include mild articulation quirks, infant feeding struggles, dental spacing issues, or oral fatigue. What it won't do is get worse over time or turn into a stutter.
At what age do late talkers talk?
Most late talkers start putting two-word combinations together between ages two and three. If a child still isn't combining words by three, that's the point to get a professional evaluation done.
What age is best to fix a tongue tie?
The zero-to-three-month window offers the easiest release and the strongest feeding results. When speech is the concern, four to seven is often the sweet spot because articulation work can happen right alongside recovery while the brain is still highly adaptable.
Final Thoughts
So, back to the original question: does tongue tie affect speech? Sometimes it does, but it gets blamed for a lot of things it isn't actually responsible for. Tongue tie muddles specific sounds. It does not create blocks, repetitions, or the interrupted flow that defines stuttering. If what you or your child is really dealing with is disfluency rather than distortion, no surgery will fix it. The right path is a neuroscience-based approach that changes how the brain builds speech. Nail down the correct diagnosis first, then commit to the treatment that actually matches the real cause.
Ready to Put This Into Practice?
Download the app and start practicing today
Reading is the first step. Real progress comes from consistent daily practice. Use StopStutter to build confidence and improve your speech every day.


