


ReviewSeptember 16, 2026
Dysarthria: Meaning, Causes of Slurred Speech, Types and Treatment
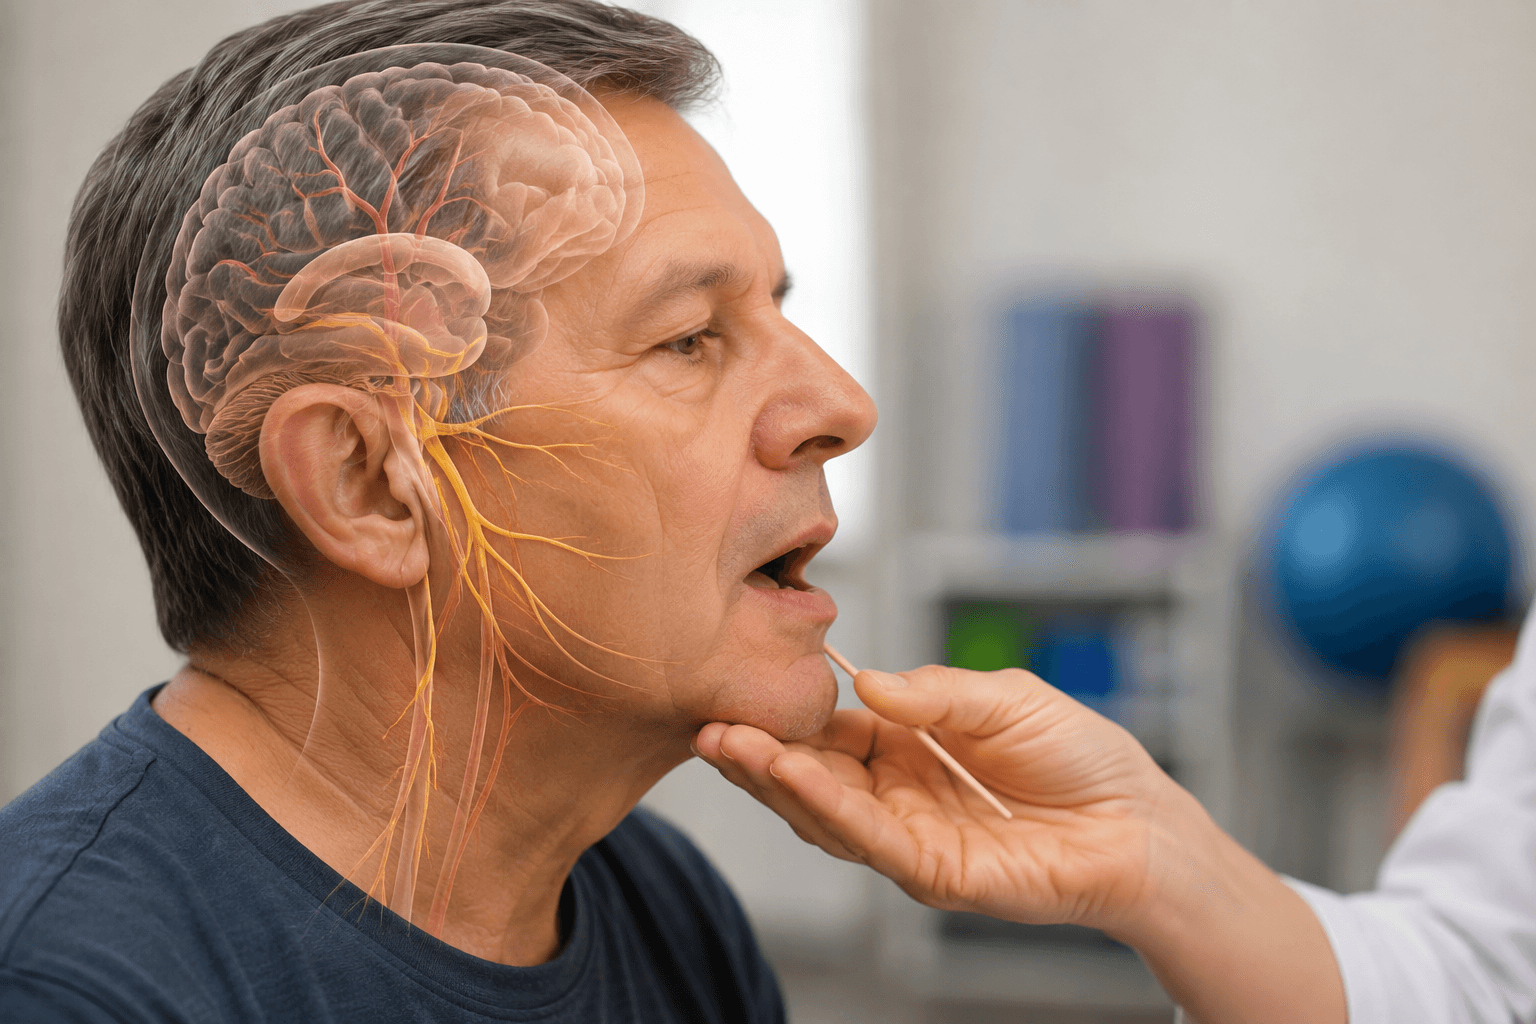
Dysarthria is a motor speech disorder. It happens when the muscles you use to speak (your lips, tongue, jaw, vocal cords, even the muscles that help you breathe) get weak or stop working together the way they should. Speech ends up slurred, mumbled or too soft to hear.
If slurred speech comes on suddenly, treat it as a possible stroke and call your local emergency number right away. Do not wait to see if it passes. See the emergency section below.
What surprises a lot of families is that the person’s thinking is fine. They know the word they want. They can hear the sentence in their head. It just doesn’t come out right.
It usually shows up after something affects the nervous system, most often a stroke, Parkinson’s, ALS, MS, cerebral palsy or a head injury. Below we cover what dysarthria and dysarthric speech mean, the seven types, the causes of slurred speech, ICD-10 codes, treatment, and how to tell it apart from stuttering. That last part is close to home for us, since stuttering is what we work on every day at the World Stop Stuttering Association.
Dysarthria Meaning and Definition
The word comes from Greek and roughly means “difficult articulation.” In medical terms, dysarthria is a neurological speech disorder. The trouble is in the muscles that produce speech, or in the nerves that control them. Language itself isn’t affected.
If someone loses the ability to speak entirely, doctors call it anarthria. That’s why you’ll often see “dysarthria and anarthria” written together on medical records.
A person with dysarthria still understands everything you say. Their vocabulary hasn’t gone anywhere, and neither has their intelligence. What changes is the sound. Depending on which part of the nervous system is involved, breathing, voice, the nasal quality of speech and how clearly each sound is formed can all be affected.
Severity varies a lot. With mild dysarthria, a few consonants might sound a little soft and a stranger probably wouldn’t notice. Severe dysarthria can make speech hard to follow even for close family.
Dysarthric Speech Meaning
“Dysarthric speech” simply means speech that is affected by dysarthria. “Dysarthric” is the adjective. Dysarthric speech can sound:
Slurred or mushy, with blurred consonants
Slow, or sometimes unusually fast
Quiet, breathy, hoarse or strained
Flat, with little rise and fall in pitch
Nasal, as if the nose is blocked or air is escaping through it
Uneven in loudness or rhythm
“Slurred speech” and “slurred speaking” are everyday ways of describing the same sound. Slurred speech is a symptom, not a diagnosis. Dysarthria is one medical explanation for it, but not the only one. See the causes below.
If you’re trying to sort out whether what you’re dealing with is dysarthria or a fluency issue like stuttering, how to stop stuttering covers the flow-based speech problems that get commonly confused with motor speech disorders like this one. Both involve the nervous system, and both can improve with the right kind of practice.
Understanding what’s happening in the brain during dysarthria matters because it changes how you approach recovery. Work rooted in neuroscience and neuroplasticity research, including the neuroscience method we use for stuttering, keeps showing the same thing: the brain, even after damage, can adapt and rebuild some pathways with the right kind of practice. That principle sits at the heart of modern dysarthria therapy.
Types of Dysarthria
Speech-language pathologists usually describe seven types. Which one a person has depends on where the damage is.
Spastic Dysarthria
Caused by damage to the upper motor neurons on both sides of the brain. You’ll see it after more than one stroke, after brain injuries and in ALS. The muscles are too tight, so speaking takes real effort. The voice sounds strained, slow and low, sometimes a little nasal.
Flaccid Dysarthria
Pretty much the opposite. Here the lower motor neurons are damaged, meaning the cranial nerves that run from the brainstem to the face, mouth and throat. The muscles go weak and floppy. Voices sound breathy, speech gets very nasal, and some people have air escaping through the nose as they talk. Brainstem strokes and myasthenia gravis are common causes.
Ataxic Dysarthria
The cerebellum is in charge of coordination, and when it’s damaged, speech loses its timing. People often say it sounds like someone who’s had a few drinks. Some speakers hit every syllable with the same heavy stress, which clinicians call “scanning speech.” MS and cerebellar strokes are behind a lot of cases.
Hypokinetic Dysarthria
This is the Parkinson’s type, linked to the basal ganglia. The voice gets softer over the years, the pitch flattens out, and words can tumble out in quick bursts. Many people with Parkinson’s don’t realize how quiet they’ve become. They just notice everyone keeps asking them to repeat themselves.
Hyperkinetic Dysarthria
Also tied to the basal ganglia, but with too much movement rather than too little. Huntington’s disease and dystonia are typical causes. Speech gets unpredictable: loud, then quiet, fast, then suddenly slow.
Unilateral Upper Motor Neuron (UUMN) Dysarthria
Plenty of older articles leave this one out. It’s caused by damage to upper motor neurons on just one side of the brain, usually from a single stroke. It’s often mild, with some slurring and weakness on one side of the face or tongue, and it tends to improve well with therapy.
Mixed Dysarthria
Two or more types at the same time. ALS often combines spastic and flaccid features. MS commonly mixes ataxic and spastic ones.
So if you’re wondering which part of the brain it affects, the answer depends on the type. It can start in the motor cortex, the basal ganglia, the cerebellum, the brainstem or the nerves leading to the speech muscles.
Dysarthria or Stuttering? How to Tell the Difference
These two get mixed up all the time. Both change the way speech sounds, and both involve the nervous system. But they’re different problems, and they’re handled differently.
With dysarthria, the issue is the muscles. Speech sounds slurred, mumbled, soft or flat, and it stays fairly consistent. It might get worse when someone’s tired, but it doesn’t really change based on who they’re talking to. It usually begins after a stroke, an injury or a neurological condition.
Stuttering is about flow. You’ll hear sounds repeated (“b-b-b-ball”), sounds stretched out (“sssso”), or silent blocks where a word just won’t start. It often gets worse under pressure, and plenty of people who stutter are completely fluent when they sing or talk to their dog. Most stuttering starts in early childhood. Core stuttering has a genetic and neurodevelopmental basis, while the fear, tension and avoidance that build up on top of it are learned and can be retrained.
Treatment overlaps, but it is not identical. Dysarthria is usually handled with speech therapy from a speech-language pathologist. Stuttering is too, using fluency-focused and mind-body approaches such as cognitive behavioral therapy (CBT) and desensitization, along with programs such as the Neuroscience Method®.
There is one place where they overlap. A stroke, a head injury or Parkinson’s can occasionally cause stuttering in an adult who never stuttered before. It’s called acquired or neurogenic stuttering, and it can show up alongside dysarthria. See neurogenic vs psychogenic stuttering. If you notice repetitions or blocks after a neurological event, mention it to the care team.
If what you’re hearing sounds more like stuttering than slurring, you don’t have to work it out alone. Our Certified Stuttering Specialists, all of whom used to stutter themselves, offer online stuttering therapy built around the Neuroscience Method®.
What the Neuroscience Method® Teaches About Rebuilding Speech
We want to be clear about this. The Neuroscience Method® was created by our founder, Lee Lovett, to help people stop stuttering. It isn’t a treatment for dysarthria, and if that’s what you’re dealing with, a speech-language pathologist should be leading your recovery. Still, some of the ideas behind it are worth knowing.
Lee built the method on neuroplasticity, the brain’s ability to keep changing and relearning for as long as we live. It has three parts. Speech Tools help in the moment. Reading Aloud fills the brain with memories of fluent speech. And Mind Training, which uses affirmations, visualization, self-talk and hypnosis, works on the fear response that starts in the amygdala.
The method targets five brain regions involved in stuttering. Two of those, the basal ganglia and the motor cortex, also show up again and again in slurred and weakened speech. So it makes sense that the approach we use for stuttering shares some habits with what speech therapists ask of dysarthria patients.
The biggest one is daily practice. Lee has always said the method only works if you stick with it, and therapists say the same about dysarthria rehab. Reading aloud is another; it’s one of the most common home exercises for both. Staying calm while you practice matters too. A rushed, anxious session doesn’t stick the way a relaxed one does.
Either way, progress is slow. You won’t hear much change from one day to the next. Give it a few months, though, and most people can. Results vary from person to person.
Signs and Symptoms to Watch For
It sounds different from one person to the next, depending on the type and how severe it is. Slurred or mumbled speech is what most people notice first. Some talk much slower than they used to. Others speed up without realizing it.
The voice often changes too. It can get quiet, hoarse, breathy or strained, or lose its natural rise and fall so everything sounds flat. Some people sound nasal, like they have a cold that never clears. Moving the tongue or face can feel harder, and drooling or trouble swallowing often comes along with it.
The emotional side is just as real. Plenty of people start dodging phone calls, stay quiet in group conversations and slowly lose confidence. People who stutter often describe the same pattern, which is why rebuilding confidence is such a big part of our work.
Slurred Speech: When It Is an Emergency
Sudden slurred speech can be a sign of a stroke or a transient ischemic attack (TIA), sometimes called a mini-stroke. Use FAST:
Face: Does one side droop when they smile?
Arms: Can they raise both arms, or does one drift down?
Speech: Is it slurred, garbled or hard to understand?
Time: Call your local emergency number right away.
Also call for emergency help if slurred speech comes with sudden confusion, a severe headache, vision loss or double vision, trouble walking or keeping balance, trouble breathing or swallowing, or after a head injury or seizure.
Do not wait to see if it passes, even if the symptoms clear up. A TIA can come before a full stroke. Do not drive yourself to the hospital.
When to See a Doctor (Not an Emergency)
Book a medical visit soon if slurred speaking:
Is new for you and has no clear explanation
Keeps coming back
Slowly gets worse over days or weeks
Comes with weakness, twitching, tremor, drooling, trouble swallowing or changes in your voice
Causes of Slurred Speech and Dysarthria
Nervous System Causes
Dysarthria isn’t a disease by itself. It’s a sign that something has affected the nervous system.
Stroke is probably the most common cause, whether it’s a blocked blood vessel or a bleed. Parkinson’s is the classic cause of the hypokinetic type. ALS usually leads to a mixed form, and MS can cause different types depending on where the lesions are.
It can also follow a traumatic brain injury from a fall, a car accident or sport. Cerebral palsy causes it from childhood. Brain tumors, Huntington’s disease and muscular dystrophy are other causes, and some medications affect muscle control enough to slur speech.
Other Causes of Slurred Speaking
Not every case of slurred speech is dysarthria. Other causes include:
Alcohol and drugs: Intoxication is a common, temporary cause.
Medications: Sedatives, sleeping pills, opioids and some seizure medicines can slur speech, especially when you start them or raise the dose. Never stop a medicine on your own. Ask your doctor or pharmacist.
Low blood sugar: Slurred speech with sweating, shakiness or confusion can mean hypoglycemia, particularly in people with diabetes.
Migraine: Some people have speech changes during a migraine aura. Get it checked the first time it happens.
Seizures: Speech can be slurred during or after a seizure.
Serious illness: Severe infections, including infections of the brain, and imbalances in body chemistry such as low blood sodium can affect speech.
Mouth and face problems: Bell’s palsy, dental problems, numbness after dental work or ill-fitting dentures can make speech sound slurred.
Exhaustion and strong emotion: Extreme tiredness or stress can briefly blur speech. Anxiety can cause shaky or rushed speech and a dry mouth, which may sound slurred. See speech anxiety. If it keeps happening, get it checked.
Dysarthria After Stroke
This is one of the situations we hear about most. Slurred speech often appears in the first few days after a stroke. The biggest gains usually come in the first three to six months of rehab, and many people keep improving after that, just more slowly.
Recovery tends to go better when speech, physical and occupational therapy work together, and support from family makes a real difference. The brain can find new routes around the damaged area, which is why those early months are such an important time to practice.
Dysarthria Clumsy Hand Syndrome
This is one of the classic lacunar stroke syndromes. A lacunar stroke is a small one, deep inside the brain, often in the pons or the internal capsule. The person ends up with slurred speech and a hand that feels clumsy or weak, usually with a bit of facial weakness on the same side.
Because the damaged area is so small, the outlook is usually good. Many people notice their speech improving within a few weeks or months.
Dysarthria ICD-10 Codes
The ICD-10 code for dysarthria is R47.1, listed as “dysarthria and anarthria.” The WHO version uses the same code, so in Brazil and Spanish-speaking countries you’ll see it as CID-10 R47.1.
R47.1: Dysarthria and anarthria, including unspecified dysarthria
I69.322: Dysarthria following cerebral infarction (ischemic stroke)
I69.122: Dysarthria following nontraumatic intracerebral hemorrhage
I69.022: Dysarthria following nontraumatic subarachnoid hemorrhage
G20.A1 to G20.C: Parkinson’s disease codes, used alongside R47.1 when dysarthria is documented. Since October 2023, the old G20 code can’t be billed on its own in the US.
Stroke coding confuses a lot of people. If dysarthria shows up while the patient is still in the acute phase, it’s usually coded as R47.1 with the acute stroke code. If it’s a lasting effect of a stroke that already happened, the I69 sequela codes like I69.322 are used instead. Guidelines get updated, so check with your billing team before submitting.
How It’s Diagnosed and Assessed
Usually two professionals are involved. A doctor, often a neurologist, looks for the cause with a neurological exam and scans like an MRI. A speech-language pathologist then figures out the type and how severe it is.
The speech assessment is pretty hands-on. The therapist watches how your lips, tongue, jaw and soft palate move. You’ll be asked to hold an “ahh” as long as you can, read a short passage, and say “pa-ta-ka” as fast as possible. (Therapists call these AMRs and SMRs, short for alternating and sequential motion rates.) They’ll also listen closely to your breathing and voice, because that’s where a lot of problems start.
Many therapists use standard tests as well. The two you’ll hear about most are the Frenchay Dysarthria Assessment, now in its second edition (FDA-2), and the Assessment of Intelligibility of Dysarthric Speech, usually called AIDS.
Getting the type right shapes the whole treatment plan, so this step matters more than people expect.
Treatment and Speech Therapy
There’s no one-size-fits-all treatment. It depends on the type, the cause and how severe things are.
Almost everyone starts with speech therapy. A speech-language pathologist works on breathing, clearer sounds, pacing and voice. For Parkinson’s, a program called LSVT LOUD has a strong track record. It trains people to speak louder through short bursts of intensive practice.
Breath support is often the first step, since speech runs on air. After that, therapists may teach pacing, which means slowing down so the muscles have time to coordinate, and clear speech strategies, where you deliberately overpronounce each sound. Some also use oral motor exercises for the lips, tongue and jaw. The evidence on those is mixed, so most therapists pair them with real speaking practice.
Treating the cause matters too. A doctor may adjust a medication that slurs speech or manage the underlying condition, such as Parkinson’s disease.
Whatever the approach, short and calm practice every day is what makes it stick. For people whose speech is too affected to rely on, AAC devices like tablets or communication boards can fill the gap.
Many insurance plans cover at least part of speech therapy when it’s medically necessary, especially after a stroke, so it’s worth checking your policy before you start.
Dysarthria Exercises for Adults
These exercises are for people who already have a dysarthria diagnosis. If your slurred speech is new and unexplained, see a doctor first.
Most of the real progress happens at home, between sessions. Your therapist will tailor exercises to your specific type, but these come up the most.
Start with breathing. Take a slow breath in, then let it out on a long, steady “sss,” or count as high as you can on one breath. If the breath is weak, everything else will be too.
Next, the voice. Hold an “ahh” at a strong, comfortable volume and see how long you can keep it steady. Counting from 1 to 20 a little louder than feels natural also helps. It’s the same basic idea as LSVT LOUD.
For clearer sounds, say “pa,” “ta” and “ka” one at a time, then together as “pa-ta-ka.” Aim for clean sounds, not speed.
Reading aloud may be the most useful one here. Pick a short passage and read it slowly every day, giving each syllable its full shape. It’s also one of the three pillars of the Neuroscience Method® for stuttering, for many of the same reasons.
A mirror helps too. Watching your lips and jaw makes it easier to catch sounds that are getting lazy.
Don’t overdo it. Ten minutes every day beats an hour on a Sunday.
Dysarthria in Children
Childhood dysarthria, sometimes called pediatric dysarthria, is less common than in adults, but it does happen. Cerebral palsy is the most common cause. It can also come from genetic conditions that affect the nervous system, a brain injury, a brain tumor or complications during birth.
Starting early really matters with kids. A young brain is more flexible, so there’s more room to build new pathways. If you’re unsure whether your child needs an evaluation, a pediatric speech-language pathologist can usually tell you quickly. Sudden slurred speech in a child needs urgent medical care.
Parents sometimes worry about dysarthria when their child is actually stuttering. If your child repeats sounds, stretches words out, or gets stuck at the start of a sentence, that points more toward stuttering.
Dysarthria vs Aphasia vs Dysphasia
These words sound so alike that people mix them up constantly.
Dysarthria is a muscle problem. The person knows exactly what they want to say but can’t get it out clearly. Aphasia is a language problem, so finding words, understanding others or building sentences gets hard. Dysphasia means more or less the same as aphasia, though you’ll see the word less these days.
Then there’s dysphagia, with a “g.” That’s about swallowing, not speech, and it often turns up alongside dysarthria after a stroke.
Losing the voice itself, down to a whisper, is a different problem called aphonia. See psychogenic aphonia.
A stroke can cause any of these, sometimes more than one at once, and each is treated differently.
Frequently Asked Questions
What does dysarthric speech mean?
Dysarthric speech is speech affected by dysarthria. It can sound slurred, slow, quiet, flat or nasal because the muscles used for speaking are weak or poorly controlled.
What causes slurred speech?
The most common serious causes are stroke, brain injury, Parkinson’s, ALS, MS and brain tumors. Alcohol, medications, low blood sugar, migraine, seizures and illness can also cause it, so get it checked.
When is slurred speech an emergency?
When it comes on suddenly, especially with face drooping, arm weakness, confusion, severe headache or vision loss. Call your local emergency number right away. Do not wait to see if it passes.
What is an example of dysarthria?
Picture someone with Parkinson’s whose voice has gotten so soft that nobody at the dinner table can hear them. Or a stroke survivor who knows exactly what they want to say, but it comes out slow and slurred.
Will dysarthria go away, and can it be cured?
That depends on the cause. After a stroke or brain injury, many people improve a lot with therapy, especially in the first six months, and mild cases can almost fully clear up. With conditions that get worse over time, like Parkinson’s or ALS, there’s no cure, but therapy and regular practice can help keep speech clearer for longer.
Can a stroke cause stuttering as well as dysarthria?
Yes. It’s called acquired or neurogenic stuttering, and it sometimes appears together with dysarthria. It sounds different, more repeating and blocking than slurring, so bring it up with your care team if you notice it.
Final Thoughts
People misread dysarthria all the time. Someone slurring their words gets taken for drunk, or confused, or just unfriendly, when really their nervous system has been through something serious. They’re still fully themselves. Their speech just isn’t cooperating.
If you or someone you love was recently diagnosed, get in touch with a speech-language pathologist early. Practice a little every day. And be patient. The brain can adapt more than most people expect, even if it takes a while to show.
Ready to Put This Into Practice?
Download the app and start practicing today
Reading is the first step. Real progress comes from consistent daily practice. Use StopStutter to build confidence and improve your speech every day.


